CONDITIONS
Fibromyalgia Syndrome (FMS)
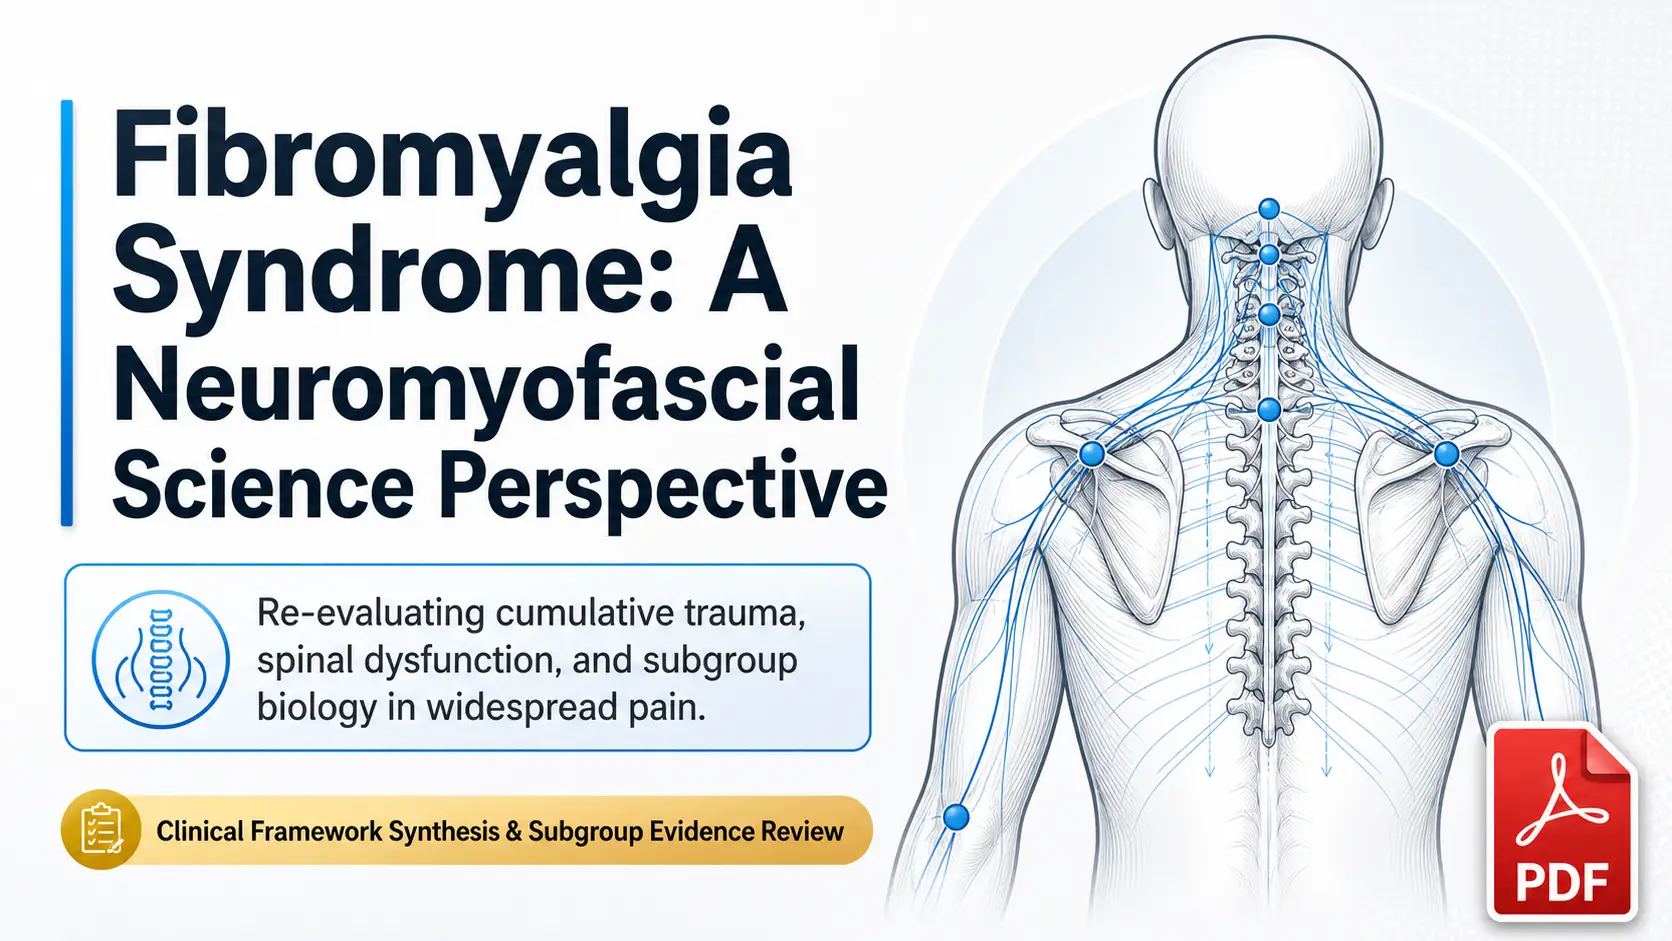
Fibromyalgia feels widespread and all-consuming. Fatigue, pain everywhere, and symptoms that seem completely disconnected from one another. The challenge is that fibromyalgia is labeled as a syndrome, not a disease, which means it describes a collection of symptoms without necessarily identifying what is driving them. NMF Science investigates whether fibromyalgia often masks specific, identifiable neuromyofascial and neuropathic drivers in the spine and limbs. When those drivers are found and mapped precisely, they can become the foundation for more targeted care.
Current Medical Understanding
Fibromyalgia is typically described as widespread chronic pain accompanied by fatigue, sleep disturbance, and cognitive difficulties often referred to as brain fog. The condition is diagnosed using symptom criteria established by the American College of Rheumatology, involving tender point testing and symptom questionnaires. Standard treatments include anti-inflammatory medications, antidepressants, physical therapy, and lifestyle modifications.
Many people improve only partially with these approaches. MRI imaging often shows mild degenerative changes but rarely reveals pathology severe enough to fully explain the extent of symptoms. Because imaging frequently appears normal or near normal, fibromyalgia has historically been described as a centralized pain condition, meaning the problem is attributed to how the brain processes pain rather than to identifiable tissue pathology. For many patients, this framing leaves them without a clear path forward.
It is worth noting that this picture is shifting. Multiple independent peer-reviewed studies now describe measurable objective biological subgroups within the fibromyalgia population, including patients with documented small-fiber nerve damage, active myofascial trigger points that reproduce widespread pain patterns, and autonomic nervous system dysfunction. Fibromyalgia is not purely subjective, and it may not be a single uniform condition.
NMF Science Perspective
NMF Science views fibromyalgia not as a single disease but as a syndrome label that may obscure highly specific, localized biological drivers. The investigational question is not "why is the brain amplifying pain signals" but rather "what physical injury pattern could be flooding the nervous system and creating the appearance of central sensitization."
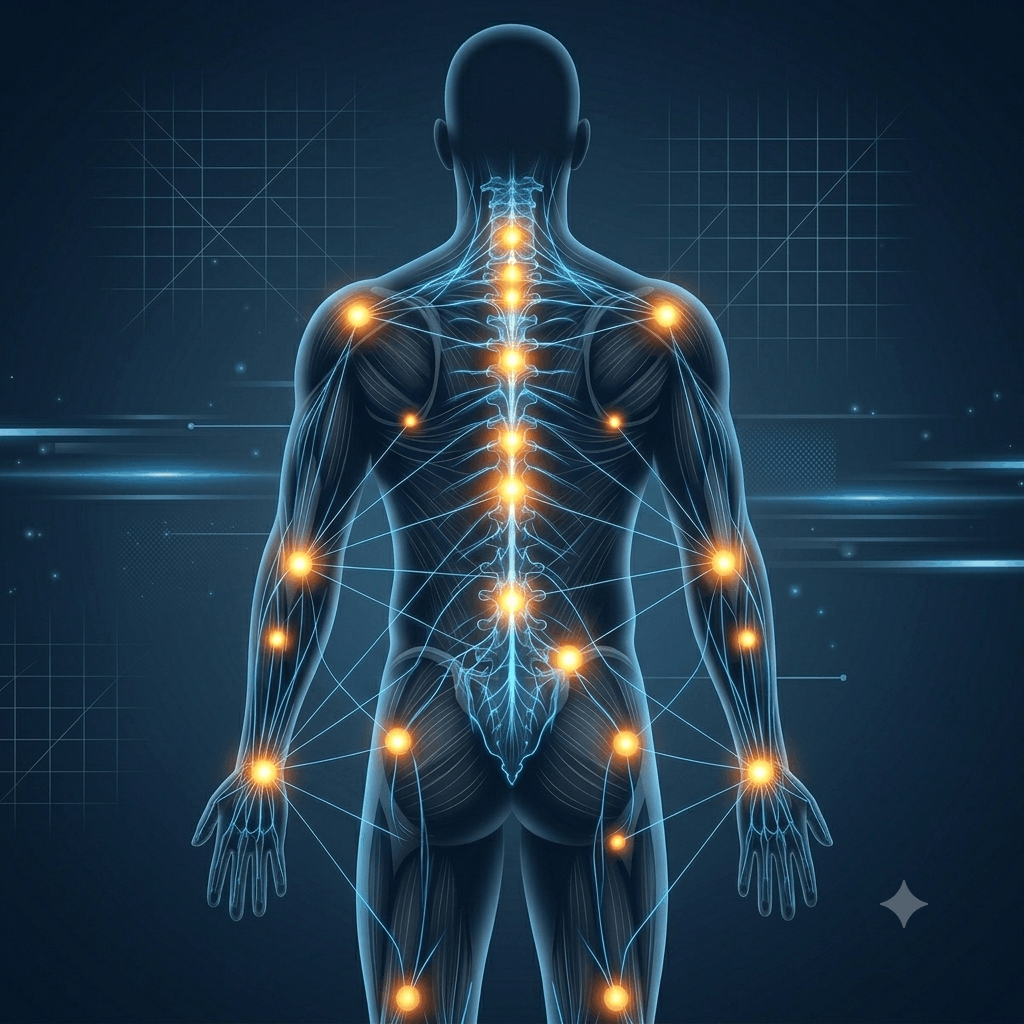
Clinical histories across fibromyalgia patients reveal a recurring pattern. A significant portion carry a history of cumulative mechanical stress, repetitive injury, or distinct physical trauma. Clinical observations suggest these physical traumas may accumulate over time, manifesting as localized neuromyofascial injuries that cluster at high-stress biomechanical junctions along the spine. The key junctions NMF Science identifies are the craniocervical junction where the neck meets the skull, the lower cervical spine from C5 to T1, the thoracolumbar junction around the mid-back, and the lumbosacral junction in the lower back.
Pathology does not need to be present at all four of these junctions. Clinical observations indicate that involvement of the cervical spine combined with at least two other junction points is often sufficient to generate the widespread symptom profile that meets fibromyalgia diagnostic criteria.
The working hypothesis is that when neuromyofascial fibrosis develops at these junctions, it may compress and irritate adjacent nerve roots and neural pathways. This could create subclinical neuropathies producing pain and sensory dysfunction along nerve distributions without the presence of an obvious disc herniation visible on standard imaging. NMF Science proposes that the diffuse, seemingly systemic pain characteristic of fibromyalgia may in some patients originate from these hyper-localized mechanical injuries acting as constant physical irritants anchored along the spinal axis.
Autonomic nervous system involvement may also help explain the non-pain symptoms that many fibromyalgia patients find most disabling. Palpitations, breathing changes, bowel and bladder dysfunction, orthostatic symptoms, and allergy-like responses are well documented in this population. Peer-reviewed research confirms that measurable autonomic dysfunction occurs in fibromyalgia, including studies by Puri and Lee (2022) using the COMPASS 31 instrument and by Falco et al. (2024) documenting autonomic small-fiber pathology on skin biopsy. Whether cervical and thoracic neuromyofascial pathology contributes to these autonomic findings is a question the NMF Science framework investigates, and it has not been established in the published literature.
The NMF Science approach to fibromyalgia is to work backward from the symptoms. Rather than treating fibromyalgia as a single entity requiring a uniform protocol, each patient's specific symptoms are traced back to identify possible neurological or neuromyofascial drivers in the spine or limbs. That process builds a patient-specific map. The map is what makes more targeted, individualized care possible.
This does not mean fibromyalgia is not real. It means the label may be obscuring something more specific that deserves a more precise investigation.
A Clinical Pattern Worth Noting
One of the most consistent clinical observations in fibromyalgia patients evaluated through the NMF Science framework is how many of their seemingly disconnected symptoms appear to trace back to shared spinal drivers. A patient presenting with migraines, TMJ pain, carpal tunnel symptoms, sciatica, and irritable bowel syndrome may appear to have five separate conditions. Through neuromyofascial mapping, these sometimes emerge as possible downstream effects of multi-level spinal pathology at the same junction points described above.
This pattern matters because it changes the investigational approach entirely. Instead of evaluating each symptom in isolation, the framework asks what single or multi-level spinal injury pattern could be producing all of these symptoms simultaneously. Identifying that driver may do more than address one complaint. It may shift the wider symptom map.
It is also important to note what the NMF Science framework does not claim. It does not assert that all fibromyalgia has the same cause, nor that every patient has identifiable spinal pathology as a driver. The framework proposes that a meaningful subset of patients diagnosed with fibromyalgia may have under-recognized neuromyofascial injury patterns that deserve more precise evaluation. That evaluation begins with mapping.
What We Investigate
→ History of significant physical trauma, accidents, repetitive strain, or chronic mechanical stress that may have initiated cumulative spinal pathology.
→ Neuromyofascial dysfunction at the four key spinal junctions: craniocervical, lower cervical (C5-T1), thoracolumbar, and lumbosacral.
→ Subclinical nerve root irritation (radicular effects) or spinal cord involvement (myelopathic effects) that may not appear as severe pathology on standard MRI.
→ Active myofascial trigger points and muscle tightness patterns and whether they correlate with the patient's specific widespread pain distribution.
→ Small-fiber nerve involvement contributing to paresthesias, numbness, tingling, or sensory disturbance across the limbs and face.
→ Autonomic nervous system dysfunction associated with palpitations, orthostatic symptoms, bowel and bladder issues, or breathing changes.
→ Whether seemingly disconnected symptoms such as migraine, TMJ pain, carpal tunnel, sciatica, and anxiety trace back to shared spinal drivers on the patient-specific neuromyofascial map.
→ Structural findings on bimanual physical examination including retrolisthesis, malrotation, loss of segmental movement, and areas of localized fibrosis that standard imaging may not capture.
→ Whether the patient's symptom timeline suggests structural pathology that has not yet become visible on MRI.
→ Treatment response patterns: whether specific symptoms improve with targeted neuromyofascial intervention, and what that response reveals about the structural factors contributing to the overall symptom map.
Learn More About Fibromyalgia Syndrome
Below you will find our most comprehensive educational resources on Fibromyalgia Syndrome and the NMF Science investigational perspective. Explore detailed video explanations, clinical slideshows, and in-depth articles examining what neuromyofascial mapping adds to our understanding of this complex and frequently misunderstood condition.
Videos
Slideshows